



(Texte français disponible ici)
I’ll start you off with a few appetizers. Then we’ll get to the main course.
OK, let’s dive in!
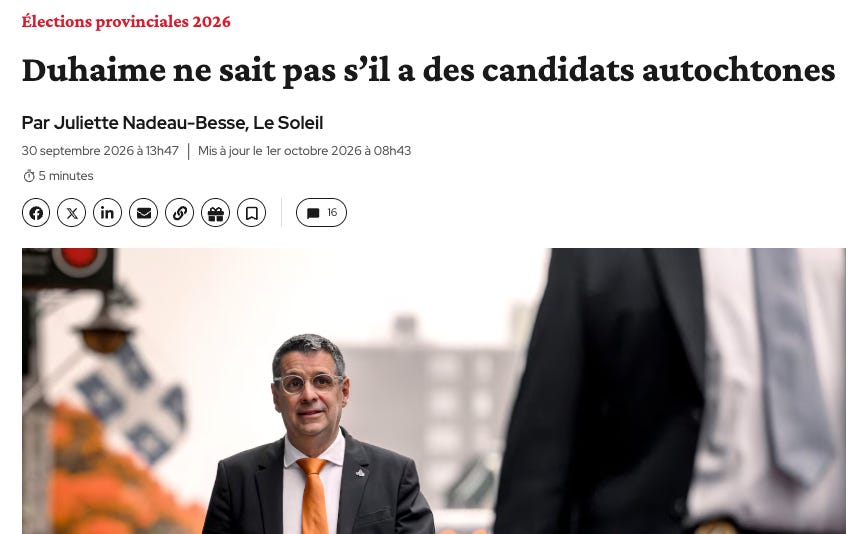
Éric Duhaime doesn’t know if any of his candidates are Indigenous
LOL
“Honestly, I haven’t asked my candidates whether they have Indigenous roots,” Éric Duhaime admitted at a news conference, according to the article in Le Soleil.
LOL
You can generally remove both the adverb “honestly” and the “honesty” from any politician’s answer that starts with “honestly.”
Of course he knows. And if there were any, he’d know that too. It’s just less embarrassing to answer that way.
Today’s pot-calling-the-kettle-black quote
“He doesn’t understand economics.”
— Christine Fréchette, leader of the soon-to-be-defunct Team Christine Fréchette, on Paul St-Pierre Plamondon.
Christine, with all due respect, neither do you.
Re: Northvolt, Nemaska Lithium, Lion Electric, Flying Whales, Recyclage Varennes…
The last CAQ man standing
Projections from polling aggregator Route 127 show Bernard Drainville neck and neck with the QCP candidate in his riding of Lévis.
Which means he might survive.
Imagine the scenario. The PQ wins 63 seats, one short of a majority. Bernard Drainville is the CAQ’s only elected MNA, making him the de facto leader of a party that still has millions in the bank and can therefore survive for a long time, even with a token presence in the legislature.
Whether a referendum is held would then depend entirely on whether our very own Bernard decides to return to his former party.
That would be fantastic.
The QCP promises private hospitals
Yesterday, I explained that the QCP had already won the election by pulling most of the other parties toward it, particularly the one that will form the government, reshaping Quebec politics as no party has in 30 years.
That’s not an endorsement of the QCP’s platform, much less of some of its candidates, who are steeped in conspiracy theories. Nor is it an endorsement of their leader and his penchant for making up or twisting facts when reality might prove him wrong.
(Yes, I know, PSPP and Christine Fréchette do it too. I’ve pointed out examples in this campaign journal.)
I don’t like the QCP’s methods or tone, its habit of targeting vulnerable groups, or its general lack of empathy (yes, yes, PSPP too).
I’m no fonder of Éric Duhaime’s complete lack of scruples. He had no qualms about riding the wave of disinformation during the pandemic to recruit members and raise money. Using anger, ignorance, and resentment as political fuel rarely ends well.
Today, Mr. Duhaime said he wants to build and operate four private hospitals in Quebec: one in Quebec City, one in Montreal, and two others in locations he hasn’t specified.
I agree.
😱
I actually think it’s a very good idea.
😱😱😱
Before we go any further, just a heads-up: my knee’s acting up today after an injection yesterday, so I typed the rest comfortably seated in my armchair, icing it from time to time.
There’ll be fewer reference links than usual because constantly switching windows on an iPad is a pain. I’ll include two at the end, if you’re good.
I’ve worked extensively on health policy and could talk about it for hours. We’ll try to keep this interesting, because there’s an opportunity to make decisions that could reshape the system and make a real difference to the care available over the next few years.
But first, we need to work through a few preconceptions.
Buckle up. Here we go!
+++++++
For many people, private involvement in health care is a matter of ideology. The right is for it, because… The left is against it, because… Each camp sees the issue through the lens of its own preferences and reaches the conclusions it wants.
Health care is extraordinarily complex, so you can always find examples that confirm your preconceptions.
You’ll easily find a stack of studies concluding that privately delivered care kills patients, and others concluding that it practically stops them from getting sick.
It gets downright confusing, because you also have to sort through the methodologies. Not everything is comparable, and bad studies do exist.
I’m not against studies. I like studies. I’ve tracked down and read a ton for my own publications and for others I’ve edited. Many are useful. Others just add noise.
I’ve worked at think tanks on the right, in the centre, and on the left. I’ve seen competent, rigorous people on the right, in the centre, and on the left.
I’ve seen less competent people on the right and the left, more often than in the centre, because overall competence tends to decline as you move closer to the ideological extremes, with convictions getting in the way of reasonably impartial reasoning.
I’ve also pored over enough studies on subjects I know well enough to spot glaring flaws in their premises or methodology. Researchers often have extraordinarily detailed knowledge of their field and tunnel vision about everything else. I’ve also corrected researchers who had misinterpreted the very figures they were citing.
(I’m not saying this to brag. I’m lucky to have an eclectic background. I’m not good at anything, but I’m not terrible at anything either. Well, almost. At our place, my spouse handles the DIY. Less risk of injuries and, above all, damage to the decor.)
Citing a study doesn’t guarantee that it’s conclusive, or that a conclusive study supports the conclusions being drawn from it.
It can be confusing as hell.
I’m ideologically agnostic, so I rarely have strong convictions about the best way to achieve the goal. I leave the ideological feuds to others.
But I do have one fundamental conviction about the goal: health coverage should be universal and organized so that everyone can get care when they need it.
Having owned a business in another life (I mean a previous career, not reincarnation), I don’t tend to see entrepreneurs as money-hungry vampires by default. I see them as innovators who look at a problem and see an opportunity to solve it, with profit as a possible reward.
Yes, there are crooks. That’s why we need rules.
So much for the long preamble.
You’ll find studies saying privately delivered care costs more, and others saying it costs less.
You’ll also find studies saying privately delivered care improves access, and others saying it undermines access.
Finally, you’ll find studies saying privately delivered care siphons resources from the public system, and others saying it makes better use of health care resources, ultimately increasing the amount of care that can be delivered.
All these conclusions can be true at the same time. It depends on what you’re measuring.
I prefer a different kind of study, one that takes a broad macroeconomic view. A natural experiment, if you like.
It’s called Europe.
All European countries have universal health care systems. Some resemble ours, in that the state is the single payer for care. Examples include the United Kingdom (where our health care system originated), Norway, and Sweden.
Others rely on mandatory private coverage through group plans, with the state providing coverage for people who can’t access a group plan. Examples include France, Germany, and Austria.
One thing all these systems have in common is that patients don’t go broke getting care (unlike in the United States, where a significant share of the population has inadequate coverage or none at all).
Another thing European systems have in common is that they generally outperform ours. European health care systems also generally outperform ours, as well as those in the other provinces.
Here’s the typical reaction of a Quebecer getting care in Europe.

It’s so quick you almost find yourself hoping to break something just to go back to the hospital.
One final thing these systems have in common is that the state generally isn’t the only provider of care.
That’s almost unthinkable in Quebec. In Europe, it’s always been that way.
In France, Germany, Italy, and Spain, countries with deeply rooted socialist traditions, a third or more of hospitals are private, for-profit facilities.
That doesn’t even include non-profit organizations operating outside the public sector. Even Sweden, with its strong social democratic tradition, has a few private, for-profit hospitals. There aren’t many, but one is particularly revealing: it shows how a single hospital can stand out within the system it operates in.
A few years ago, I studied St. Göran (St. George) Hospital in Stockholm, which is often cited in conservative circles.
This is St. Göran, in case you were wondering.

Apparently, Swedish saints stand 15 feet tall and, like their flocks, would hold their own in strongman competitions. But let’s carry on.
In the late 1990s, St. Göran Hospital wasn’t doing very well. Stockholm County Council, responsible for delivering health care in the capital, faced two choices: close it, or take a chance on handing its management over to a private company.
(I should note that health care is a local responsibility in Sweden. The national government sets the regulatory framework, overall funding, and rules governing the health professions, but each region decides how care is funded and delivered. We should do that here.)
Stockholm County Council chose to entrust St. Göran’s management to the Swedish multinational Capio, which has since been swallowed up by Australia’s Ramsay (which hasn’t always made good calls, but we won’t get into that today).
Under Capio, St. Göran became a remarkably high-performing hospital. Between 2000 and 2016, it nearly tripled the number of patients treated in its emergency department, from 35,000 to 85,000, a volume comparable to our largest hospitals.
More astonishing still, St. Göran achieved this and remains one of Sweden’s most frequently honoured hospitals for the quality of its care. (Sweden has hospital rankings. We should do that here too.)
It doesn’t cost patients more, because care is covered by the state, just as it is at any public hospital. In practice, and in terms of access, St. Göran has remained public. Many patients, and even some hospital employees, don’t know the hospital is run by a corporation.
It doesn’t cost the state more, because the rates for each procedure are regulated, whether it takes place in a public or private facility. (Another good idea we’re slow to adopt here, notably for specialized medical centres, or CMS, which perform day surgery funded by the RAMQ.)
Even more astonishing was the local union’s reaction. When St. Göran was handed over to Capio, a major Swedish labour federation decided to make it a symbolic fight to preserve the integrity of public services.
After a few years, the hospital’s union let the federation know that, actually, entrepreneurial management wasn’t so bad, and there were advantages to having decision-makers on site. We’ll stick with private management after all, thank you very much.
Regional indicators also showed lower absenteeism and higher staff morale, notably because bottom-up management was encouraged instead of the traditional top-down approach, which often leaves employees demotivated.
Patient satisfaction was higher too. An annual assessment of patient satisfaction is mandatory in Sweden. St. Göran’s managers thought that wasn’t enough. They introduced continuous assessment to measure patient satisfaction in real time.
When was the last time anyone here asked you how satisfied you were with your care?
Remember, I documented all this in 2017. Things don’t exactly move fast in Quebec, do they?
Other hospitals in Sweden started wondering what was in the water at St. Göran and how they could replicate its results. So did public decision-makers.
The moral of the story is that private ownership or management can produce good results when the incentives are properly aligned.
+++++++
Quebec’s relatively little-known private long-term care homes under public contract (CHSLDs) offer another example. These should not be confused with private CHSLDs operating without such contracts. They’ve shown that entrepreneurial management can produce better results with comparable funding and resources. I demonstrated this a few years ago. Economist Pierre Fortin had done so before me. (Hi, Pierre!)
What matters isn’t whether the facility is private or public, but whether we make the best possible use of the health care system’s scarce resources. Competition and good incentives can encourage that within a public, universal system. Europe provides broad evidence of it. Look closely and you’ll find all sorts of rough edges. But if we look at the overall picture, we could adopt just about any European system here, with its mix of care providers, and be better off.
What we must avoid is a parallel private system accessible only to the wealthiest. The QCP wants to take us in that direction when it says it wants to allow private insurance to cover basic medical care.
It’s easy to imagine what would happen: a parallel private system would develop, funded by those who could afford it, with care provided by doctors and other professionals who had left the public system.
We already have this problem in Quebec, with a growing number of doctors practising outside the public system and patients paying out of pocket. Opening the door to private insurers would make the problem worse. That’s what some libertarians associated with the QCP want: some for ideological reasons, others because they’re tired of waiting and think everyone should pay for their own care, since they themselves can afford it (yes, these people exist).
At a stretch, the idea might be defensible if Quebec had a surplus of doctors. Instead, Quebec faces a chronic shortage for the foreseeable future.
For doctors in “fully private” practice, outside universal public coverage, the government would be entirely justified in regulating fees for medical services, as elsewhere in the country. It should also reimburse the cost of that care so it remains accessible to everyone. And above all, no private insurance for basic care.
But for hospitals run independently under the umbrella of public coverage, Europe shows that the model could help us.
The people working in our health care system, who rightly complain about being stuck with an often inhumane employer, might benefit too.
I’ll finish by addressing two objections before they come up.
1. Yes, but what if health care workers want to leave public hospitals?
Yeah, and? If a doctor increases her productivity by 20% because surgeries aren’t being cancelled at the last minute every day, what’s the problem? So much the better if resources naturally move to where they’re put to the best use. It might wake up a few hospital managers, especially if funding is tied to the number of patients treated.
Better workplaces could also help bring back the many nurses who have left the public system in recent years, fed up and exhausted.
2. Yes, but couldn’t resources shift toward more profitable or less complex procedures, leaving oncology, for example, short of staff?
Yes, and it’s important to account for that and monitor how the availability and delivery of care change.
For now, given how many surgeons are underused and how many nurses we might be able to bring back, I wouldn’t be too worried. And we’re talking about 4 hospitals, not 40.
It could also be an opportunity to rethink how our hospitals are organized.
In Quebec, apart from the few university hospitals, each hospital has to offer a similar range of services: obstetrics, oncology, surgery, an emergency department, and so on. In the regions, where two hospitals may be 50 or 100 km apart, that makes sense. In cities, where hospitals are practically within walking distance of each other, it makes no sense.
We could have a single, larger emergency department in one of the two hospitals, better equipped to handle surges (for example, when three ambulances arrive at once during the night and there’s only one doctor on duty). And a larger obstetrics unit in the other hospital. We’d have the same number of health care workers overall, but in settings that could perform better and adapt more easily because resources and expertise would be pooled. This is already done elsewhere.
I’ve spent way too long on this, so I’ll leave it there.
Keep an eye on Éric Duhaime. But on this one, I think he’s right.
Before I forget, here are the promised links. For St. Göran, it’s here. For private long-term care homes under public contract, it’s here.
Fun fact about the second study: it’s based on data the Health Ministry (read: political advisers) would rather have kept hidden. My access-to-information request was initially denied because the data didn’t fit the governing party’s preferred policy direction. I had to appeal the decision.
When someone tells you they’re going into politics first and foremost to help you, they might be lying.
-30-
My name is Patrick Déry. I’m a French-speaking Québécois who writes for a living, and I’m trying something different here. If you enjoyed reading this article, you can support me by buying me a coffee. You can also subscribe to this publication (free or paid, your choice).
Comments, shares, and “likes” are always appreciated. They also help the Substack algorithm notice me, so don’t be shy!